Dana Carpender: What do you eat on a typical day?

4415406430_7a5ba031bb_o.jpgDana Carpender, author of several low carb cookbooks, generously gave her time to be interviewed for this blog site. Over several posts she will be sharing her wisdom about the low carb lifestyle.

My first question: What do you eat on a typical day Dana?

Honestly? Leftovers. 🙂 What with trying recipes, and only two people in the house, I eat a lot of leftovers. The summer I wrote The Low Carb Barbecue Book I ate chicken or ribs for breakfast every day for weeks.

In the absence of leftovers? Probably an omelet for breakfast, especially if there are ripe avocados in the house; cheese-and-avocado omelet with chipotle hot sauce is a big favorite of mine. Dinner will be a fairly simple protein — chicken, steak, burgers, pork steaks, something like that, with a low carb vegetable or salad with it if we feel like it. I confess we don’t always bother. If I want just a little something, I might well have shirataki with a fatty sauce – or just butter and Parmesan.

This is, of course, when I’m not working on a book. If I am, it’s a wild card! It depends on what sort of book it is, what I have in the house, what idea I’ve had.

If I snack, it’s usually on nuts. I’ve snacked less and less as the years have gone by, and as I’ve deliberately increased fat as a fraction of my calories.

Perhaps the most notable thing is that I have long since slipped away from the three-meals-a-day format. I rarely eat more than two meals a day anymore; I’m just not hungry enough. I try to do some intermittent fasting, so I often don’t eat until noon or one — a good 16 hours after I ate the previous night — although I drink copious quantities of tea.

Long-time readers will note that this violates a previously stated rule to always eat breakfast. I no longer consider that a hard-and-fast rule, but rather one that depends on circumstance. If someone works away from the house in a place where carby garbage is available, like the donuts in the break room or the candy bars in the vending machine, then I feel breakfast is imperative, even if it’s just a couple of hard boiled eggs or individually wrapped cheese chunks grabbed on the way out of the house. This is especially true for those who are just starting out, and not yet solidly in the mindset of “this is how I eat.”

But if, like me, you have more time freedom, and have achieved a blissful lack of regard for starchy, sugary stuff, postponing breakfast until you’re genuinely hungry is a good way to work in some intermittent fasting.

Too, I’ve lost the idea that some foods are “breakfast foods,” while dinner needs to be a protein and two veg. I’m perfectly happy having leftover chicken and coleslaw for breakfast, or whatever happens to be kicking around the fridge. And I’ve certainly been known to eat eggs for dinner, or just make something snack-y, like Chicken Chips. (Chicken skin spread on the broiler rack and baked until crisp, then salted. Yum. I buy 10-pound bags of chicken skin from my speciality butcher.)

One other oddity: I don’t feel any need to snack during movies or television. It’s common for people to feel that there should be something they can munch on mindlessly for hours while consuming entertainment, but low carb foods don’t lend themselves to that. They’re filling. Eat a bucket of mixed nuts the size of even a small movie theater popcorn and you’ll make yourself sick. People need to get away from the idea of food as entertainment.


 

No proven benefit to replacing saturated fat with polyunsaturated fat

19349485773_214c8033a3_bAn analysis of the Minnestota Coronary Experiment (1968-73) data has shown that there was no evidence from randomised controlled trials that the serum cholesterol lowering effects of replacing saturated fat with linoleic acid resulted in any reduction from coronary heart disease and total mortality.


The data was re-analysed by Ramsden and Zamora et al and published in the BMJ on 16 April 16.

J Lennert Veerman comments: ” A diet enriched with linolieic acid did not reduce mortality. Indeed participants had a higher mortality than controls. These unexpected results proved difficult to stomach for researchers at the time. The trial ended in 1973 but it took till 1989 for the results to be published. In the past decade old certainties about dietary fats have been questioned and some have been abandoned. Last year US dietary guidelines removed dietary cholesterol and total fat as risk factors worth worrying about.

If blood cholesterol values are not a reliable indicator of cardiovascular risk, then a careful review of the evidence that underpins dietary recommendations is warranted. Ideally recommendations should be based on clinical outcomes, not surrogates such a cholesterol concentration.

From an article in BMJ 16th March 2016

Bacon and beef gratin

minced-meat-179476_960_720

Bacon and Beef Gratin

  • Servings: 5-6
  • Difficulty: easy
  • Print

Ingredients:

  • 600g minced beef
  • 400g bacon, chopped
  • 1 large onion, finely diced
  • 3 cloves garlic crushed
  • 3 tablespoons chili sauce or sambal oelek (from Asian shop)
  • pepper
  • About 8 oz of mushrooms, sliced (enough to cover the bottom of an oven-proof dish)
  • 1 courgette cut into 2mm slices
  • Grated cheese
  • 3 eggs
  • 2 dl cream
  • 1 cup water
  • Pepper, little bit of bouillon powder

Melt butter, add onion and fry until translucent, add the bacon, continue frying for a few minutes, finally add the mince and fry it until browned, mix with all other ingredients and cook for around 10-15mins.

Grease an ovenproof dish with butter, place a layer of mushrooms in the dish, then top with the meat/bacon sauce, then top with sliced courgette and sprinkle cheese over that.

Whisk together the cream water, eggs, pepper and a little bouillon powder, pour evenly over the gratin.
Whisk together the casserole and pour this over the gratin evenly.

Bake in middle of oven for about 20-25 minutes at 225 degrees.

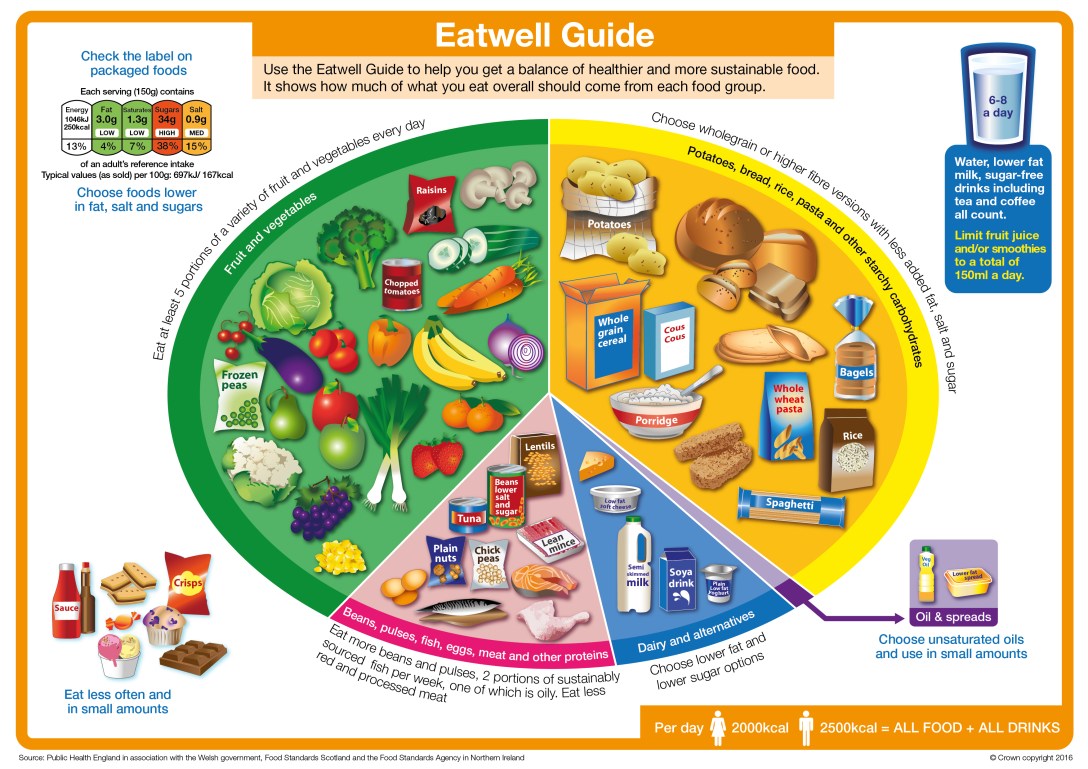
New UK “Eat Well Plate”: same old rubbish!

The UK government has released a new version of the risable “Eat well plate” which gives us at diabetesdietblog.com even more heartburn, if that were possible.

In this they have given due pominence to fruit and vegetables but have also advised even more starch such as bread, potatoes, breakfast cereals, pasta and rice. Low fat dairy is encouraged and protein is under represented again. Vegetable oil and low fat spread is given a little sliver of prominence. They have advised us to eat 30g of fibre a day and limit sugar to 30g a day.  Lordy, some of us don’t even eat this in total carbs a day! carbohydrate.jpgThey have said that 150g of fruit juice or smoothie can count as one of “your five a day”.

Cardiologist Aseem Mahhotra has tweeted, “Is this a joke?” Well, sad to say, probably not.

The government are grimly determined to back a diet that will lead to more obesity, diabetes, acid reflux, cancer and cardiovascular disease. Isn’t the NHS in enough of a mess already? Obviously the government don’t think so.


National Obesity Forum promote low carb/high fat diet at last

The National Obesity forum has published a report supporting the high fat, low carb diet for tackling the obesity and diabetes epidemic.  In response, the usual chorus of disapproval has been wheeled out to counter the report.

As supporters of the high fat, moderate protein, low carb diet we present both sides of the argument as given in today’s BBC online news, just for a bit of fun and entertainment.

The Public Health Coalition will be publishing an almost identical report when it goes live in three weeks time, not surprising since Dr Aseem Malhotra has strong links with both organisations, which have the same aims, and now are backing the same strategy.

LA2-vx06-konsthallen-skulptur

Advice to eat more fat is irresponsible and potentially deadly, Public Health England’s chief nutritionist has said.

Dr Alison Tedstone was responding to a report by the National Obesity Forum, which suggests eating fat could help cut obesity and type 2 diabetes.

The charity said promoting low-fat food had had “disastrous health consequences” and should be reversed.

Other experts have also criticised the report saying it cherry-picked and misquoted evidence.


Dr Aseem Malhotra, a senior adviser to the National Obesity Forum, said: “The change in dietary advice to promote low fat foods is perhaps the biggest mistake in modern medical history.

“We must urgently change the message to the public to reverse obesity and type 2 diabetes. Eat fat to get slim, don’t fear fat, fat is your friend.”

Risk

Dr Tedstone responded by saying: “In the face of all the evidence, calling for people to eat more fat, cut out carbs and ignore calories is irresponsible.”

She said thousands of scientific studies were considered as part of the official guidance adopted throughout the UK, whereas the National Obesity Forum quoted just 43 studies, some of which were comment pieces.

She added: “It’s a risk to the nation’s health when potentially influential voices suggest people should eat a high fat diet, especially saturated fat. Too much saturated fat in the diet increases the risk of raised cholesterol, a route to heart disease and possible death.”


Butter_curls.jpg

The report argues:

  • Eating fat does not make you fat
  • Saturated fat does not cause heart disease and full-fat dairy is probably protective
  • Processed foods labelled “low fat”, “lite”, “low cholesterol” or “proven to lower cholesterol” should be avoided
  • Starchy and refined carbohydrates should be limited to prevent and reverse type 2 diabetes
  • Optimum sugar consumption for health is zero
  • Industrial vegetable oils should be avoided
  • People should stop counting calories
  • You cannot outrun a bad diet
  • Snacking will make you fat
  • Evidence-based nutrition should be incorporated into education curricula for all healthcare professionals

The report also said humans had evolved to be a “healthy well-nourished species with a long life expectancy”, but this had gone wrong in the past 30 years.

It said there was too much focus on calories when “it is highly irrelevant how many calories a portion of food on a plate contains” and it was “untrue” that excessive calories caused obesity.

Naveed Sattar, a professor of metabolic medicine at the University of Glasgow, said the report was “good, bad and ugly”.

He backed calls to cut snacking, but said eating more fat as a cure for obesity and type 2 diabetes was “not warranted” by the evidence and would have “adverse” consequences.

He said the authors had been selective in their choice of evidence and had ignored “an abundant literature which goes against their conclusions”.

The government’s obesity adviser Prof Susan Jebb said the “current dietary advice is based on the best evidence we have”.

She said the debate should be widened from a focus on fat. “We’re eating too many calories – if we want to tackle obesity people do need to eat fewer calories [and] that means less fat and less sugar.”


The Faculty of Public Health’s Prof Simon Capewell said the focus on nutritional guidelines was “a huge distraction from the real causes of obesity” such as advertising cheap junk food to children.

And he said he was worried that the National Obesity Forum report “is not peer reviewed and does not indicate who wrote it or how it was funded”.

The National Obesity Forum says it is an independent organisation that receives professional and financial support from the food industry, pharmaceutical companies and medical bodies.

Dr Nita Forouhi, says the contains some important omissions and some references had been misrepresented such as the recommendations around vegetable oils.

The scientist, at the MRC epidemiology unit at the University of Cambridge, told the BBC: “This is a highly selective review, it is not a systematic appraisal of the evidence and in places opinions are expressed that are not backed up by a body of evidence.”

She praised the call to lower refined carbohydrates, but said the overall message to cut carbs ignored the issue of quality as “we do need wholegrain carbs and fibre in out diet”.

Prof Tom Sanders from King’s College London said: “It is not helpful to slag off the sensible dietary advice.

“The harsh criticism of current dietary guidelines meted out in this report is not justified as few people adhere to these guidelines anyway.

“There is good evidence that those that do follow the guidelines have less weight gain and better health outcomes.”


Freestyle Libre: continuous blood sugar monitor available in the UK

Freestyle have released the first reasonably priced continuous blood sugar monitor in the UK. Unfortunately it is not yet available on the NHS. You can purchase it for £157 and get extra sensors which each last two weeks for just short of £60 each.

Most blood test strips cost between 30p and 50p each. Most type one diabetics will be using 5 or more test strips a day. This costs £9,125 per person based on 5 strips at 50p each. A years supply of sensors for the Freestyle Libre will cost £1,508 so you can see that it has been priced fairly reasonably.

The new system works by having a sensor, about the size of a ten pence piece, inserted in the triceps area of the upper arm for up to two weeks at time. The adhesive is strong enough to withstand daily baths, showers and swimming activities. After an hour the new sensor is good to go.

After initial programming with your personal blood sugar targets, the mobile phone sized monitor picks up not only your blood sugar but shows the trend in which it is directed by means of directional arrows. This is perhaps the most important feature of the new machine. It would be really helpful for most people to know this when they are about to drive for instance, or if they are trying to address rising blood sugars during an attack of flu.

The number of times you can check your blood sugar with the Freestyle Libre is limitless and there are well designed graphics to show you how your blood sugars have performed over time.

80% of the costs of diabetes on the NHS is related to the treatment of complications. It seems to me that it would be money well spent for the NHS to invest in this new technology that can help diabetics control hypoglycaemia better as well as helping them keep their blood sugars in range and avoid high blood sugars. DTR_Libre_6995.jpg


Tomato Basil Cream Chicken

Lots of basil and tomatoes in season right now, enjoy!

nourishedpeach's avatar

SONY DSC

This is something I make fairly often and realized just this week that I have yet to share the recipe with you.  You’ll have it on the table in the blink of an eye and it may be devoured just as quickly, too.

This Tomato Basil Cream Chicken is the perfect dish for those times when you are wanting yummy tomato flavor but are unable to get your hands on delicious, home-grown varieties.  Store-purchased roma tomatoes are all you need-sounds blah, no?  But let me just tell you how this whole deal works…I’m sure I can convince you to get the “blah” out of your brain…

View original post 492 more words

Eggs make a good start to the day


Eggs have been shown to improve satiety and increase circulating HDL. They contain nutrients that may reduce the risk of T2D and CVD. Current guidelines regarding egg consumption and dietary cholesterol intake differ among countries: Australia recommends a max of 6 egg/wk for people with T2D. The US recommends that patients with T2D limit dietary cholesterol to <300 mg/d and <4 eggs/wk; and the UK has no suggested limit, but they do emphasize a dietary reduction of saturated fatty acids. Previous studies regarding the effect of a high-egg diet had confounding factors and/or limitations with respect to data. Australian researchers decided to address those limitations by analyzing the health effects of a high-egg diet.

In a 3-month prospective RCT, 140 patients with BMI >25 kg/m2, and either prediabetes or T2D, were randomly assigned to 2 diet groups. Patients in the high-egg group consumed 2 eggs/day for 6 days/wk, while the low-egg diet group consumed <2 eggs/wk with 10 g lean protein for breakfast. The primary outcome was change in HDL cholesterol at 3 months, while changes in anthropometric measurements, vital signs, nutritional analysis, and satisfaction were all doneeggs secondarily. Blood samples were collected for FBG, HbA1c, lipid panel, C-reative protein, apolipoprotein B, CBC, thyroid function, liver and renal function. Height and waist circumference was measured and a patient food diary was collected at baseline and 3-months. Questionnaires were used to obtain food, physical activity and quality of life information from the patients.

The study results showed that there were no significant differences in HDL from screening to 3 months between the two groups. There were also no significant differences in total cholesterol, LDL, TGs, or apolipoprotein B. Both groups had no significant differences in FBG or HbA1c. Waist circumference, total body fat, fat free mass, BP, and HR did not show any significant differences. Both group had an increase in overall satisfaction with the diets they were on. However, the high-egg group showed a higher enjoyment with the food they were eating and were less bored with food options. The high-egg group also trended toward being more satisfied with a high-egg diet compared to a low-egg diet with a significantly greater satiety and less hunger reported after breakfast.

Previous studies and current guidelines do not provide a clear message as to the whether eggs are safe and suitable as a dietary protein source for people with T2D with a high risk for CVD complications. This study showed there were no significant differences in circulating HDL, LDL, TC, or TGs between the high- and low-egg diet groups. The high-egg diet group also showed a significantly greater food-acceptability score and scored their diet with less hunger and greater satiety after breakfast; this suggest that a high-egg diet does not result in boredom and may likely improve nutritional management in patients with T2D.

Practice Pearls:
•This study compared the health effects of a high-egg diet (2 eggs/day for 6 days/wk) with a low-egg diet (<2 eggs/wjk).
•The high-egg diet group showed no significant difference in their lipid panel at 3 months, compared to the low-egg diet group.
•Test patients showed a greater satiety after breakfast and greater food-acceptability in the high-egg diet, suggesting that a high-egg diet can be used to help improve nutritional management.

NR Fuller. The effect of a high-egg diet on cardiovascular risk factors in people with type 2 diabetes: the Diabetes and Egg (DIABEGG) study –a 3-mo randomized controlled trial. Am J Clin Nutr. 2015; 101: 705-713.


Based on an article in Diabetes in Control April 2016

Dr Peter Attia’s advice on dodging death

Do you want to live to a good old age? Researcher Dr Peter Attia discussed his top tips with paleo diet enthusiast Chris Kresser in March 16. This is summary of what he had to say.

Henny Nonne (geb. Heye), Max Nonne
Professor Max Nonne und Frau [Henny Nonne], geb. Heye
There are a few obvious big things that we can all do to dodge death at a prematurely.

  1. Choose to be a non- smoker.
  2. Don’t die by suicide.
  3. Avoid accidental deaths.  Most of these are caused by three things, Road Traffic Accidents, accidental poisoning, including the wrong use of prescription medication, and falls. You can minimise these by using a seatbelt, driving carefully, particularly at junctions, not using the phone when driving and avoiding any alcohol use at all when driving.  When you are a pedestrian be wary of drivers, cross the road in safe places and be very careful regarding alcohol intake.
  4. About 80% of all deaths in the over 40s are caused by the diseases of civilisation: atheromatous disease causing heart attacks and strokes, cancer and neurodegenerative disease such as Alzheimer’s and Parkinson’s disease.  Some of these have a genetic basis that we can do nothing about, but there are lifestyle measures you can take to delay or avoid them.
  5. Keep your blood glucose and therefore blood insulin levels low and with a low level of variability. A high fat, moderate to low protein and low carbohydrate diet is best for this. Dr Attia’s opinion is that 20% carb 20% protein 60% fat is about right.
  6. Avoid stress. There are two components to this. To feel fulfilled and happy you need meaning in your life. You will be happier if you can give support to others and receive it from them too. Minimise stress if you can. Consider meditation practice.
  7. Get a good sleep every night. Sleep deprivation causes severe insulin resistance. Keep the bedroom completely dark. Keep it cool to even cold. Avoid blue light from computers, phones or lights for several hours before sleep. Consider using melatonin, phosphatidylserine, magnesium, L-threonate and vitamin D to enhance your sleep if you are not sleeping well.
  8. Exercise. This has stress benefits of its own and also improves glucose uptake into the muscles if the right exercises are done. For best increase in muscle insulin sensitivity Peter advises squats and deadlifts done with good form and with very heavy weights.
  9. Decide what you are going to do for your optimum benefit and then change your habits so that they become second nature. Repetition is the key.
  10. 151985627_f76043167b_b.jpg