
First ever guidelines for assessing and treating the diabetic foot


4276166167_e2cf9e2e47_oThe Society for Vascular Surgery, the American Podiatric Medical Association and the Society for Vascular Medicine collaboratively publish first-ever set of clinical practice guidelines for treating the diabetic foot. These  took three years to develop and are available online.


Specific areas of focus included (1) prevention of diabetic foot ulceration, (2) off-loading, (3) diagnosis of osteomyelitis, (4) wound care, and (5) peripheral arterial disease.

They include preventive recommendations such as those for adequate glycemic control, periodic foot inspection, and patient and family education.

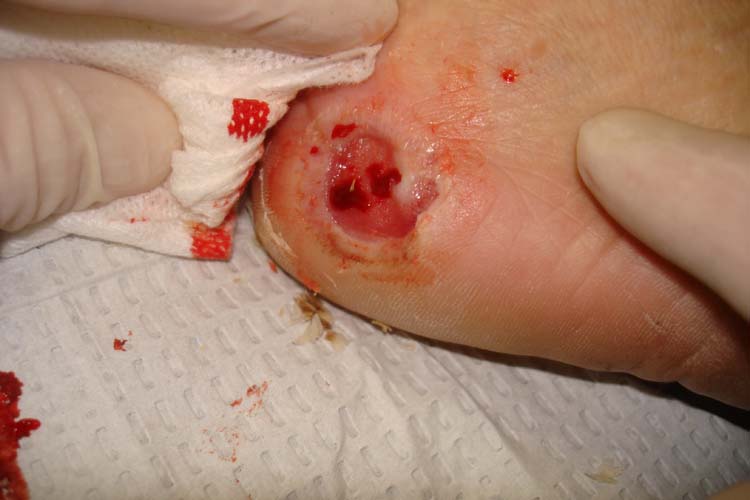
They recommend using custom therapeutic footwear in high-risk diabetic patients, including those with significant neuropathy, foot deformities, or previous amputation. In patients with plantar diabetic foot ulcer (DFU), they recommend off-loading with a total contact cast or irremovable fixed ankle walking boot.

In patients with a new DFU, they recommend probe to bone test and plain films to be followed by magnetic resonance imaging if a soft tissue abscess or osteomyelitis is suspected.

They provide recommendations on comprehensive wound care and various débridement methods. For DFUs that fail to improve (>50% wound area reduction) after a minimum of 4 weeks of standard wound therapy, they recommend adjunctive wound therapy options.

In patients with DFU who have peripheral arterial disease, they recommend revascularization by either surgical bypass or endovascular therapy.

Whereas these guidelines have addressed five key areas in the care of DFUs, they do not cover all the aspects of this complex condition. Going forward as future evidence accumulates, they plan to update recommendations accordingly.

Diabetes is one of the leading causes of chronic disease and limb loss worldwide, currently affecting 382 million people. It is predicted that by 2035, the number of reported diabetes cases will soar to 592 million. This disease affects the developing countries disproportionately as >80% of diabetes deaths occur in low- and middle-income countries.

As the number of people with diabetes is increasing globally, its consequences are worsening. The World Health Organization projects that diabetes will be the seventh leading cause of death in 2030. A further effect of the explosive growth in diabetes worldwide is that it has become one of the leading causes of limb loss. Every year, >1 million people with diabetes suffer limb loss as a result of diabetes. This means that every 20 seconds an amputation occurs in the world as an outcome of this debilitating disease. Diabetic foot disease is common, and its incidence will only increase as the population ages and the obesity epidemic continues.

Approximately 80% of diabetes-related lower extremity amputations are preceded by a foot ulcer. The patient demographics related to diabetic foot ulceration are typical for patients with long-standing diabetes. Risk factors for ulceration include neuropathy, PAD, foot deformity, limited ankle range of motion, high plantar foot pressures, minor trauma, previous ulceration or amputation, and visual impairment. Once an ulcer has developed, infection and PAD are the major factors contributing to subsequent amputation.

Available U.S. data suggest that the incidence of amputation in persons with diabetes has recently decreased; toe, foot, and below-knee amputation declined from 3.2, 1.1, and 2.1 per 1,000 diabetics, respectively, in 1993 to 1.8, 0.5, and 0.9 per 1,000 in 2009. However, including the costs of outpatient ulcer care, the annual cost of diabetic foot disease in the United States has been estimated to be at least $6 billion. A Markov modeling approach suggests that a combination of intensive glycemic control and optimal foot care is cost-effective and may even be cost-saving.

DFUs and their consequences represent a major personal tragedy for the person experiencing the ulcer and his or her family as well as a considerable financial burden on the healthcare system and society. At least one-quarter of these ulcers will not heal, and up to 28% may result in some form of amputation. Therefore, establishing diabetic foot care guidelines is crucial to ensure the most cost-effective healthcare expenditure. These guidelines need to be goal focused and properly implemented.

This progression from foot ulcer to amputation leads to several possible steps where intervention based on evidence-based guidelines may prevent major amputation. Considering the disease burden and the existing variations in care that make decision-making very challenging for patients and clinicians, the SVS, American Podiatric Medical Association, and Society for Vascular Medicine deemed the management of DFU a priority topic for clinical practice guideline development. These recommendations are meant to pertain to all people with diabetes regardless of etiology.

Practice Pearls:
•“The Management of the Diabetic Foot,” was developed after three years of studies and later published online and in print in the Journal for Vascular Surgery.
•This progression from foot ulcer to amputation lends to several possible steps where intervention based on evidence-based guidelines may prevent major amputation.
•Every year, >1 million people with diabetes suffer limb loss as a result of diabetes.

Researched and prepared by Steve Freed, BPharm, Diabetes Educator, Publisher and reviewed by Dave Joffe, BSPharm, CDE

Anil Hingorani, MD Glenn M. LaMuraglia, MD, Journal of Vascular Surgery Feb 2016 , Volume 63, Issue 2, Supplement, Pages 3S–21S

April 23rd, 2016 Diabetes in Control

Dogs improve the immune response of babies

hqdefault (6)


A Finnish study has shown that growing up with a dog in the house improves the immune response of babies. Early respiratory infections, gastroenteritis and allergic reactions are reduced.

If a man has type one diabetes his chance of passing this on to his children is one in three. Maternal type one diabetes also increases the risk of type one in children but to a much lesser degree. Genetic susceptibility is reduced to a small extent if the baby is brought up in a house where the dog lives in the house. Unfortunately cats don’t confer the same benefit.

Reported in JAMA Paediatrics 2014 and BMJ 19th July 2014

Dana Carpender: What Health Conditions Respond to Low Carb Diets?

Dana,  what is the range of health conditions that you have seen respond to a low carb diet in your readers?

The most exciting, perhaps, is polycystic ovarian syndrome, the most common cause of female infertility, and very definitely an insulin-driven illness. Back when I was still self-published, I got an email from a woman who had tried for years to get pregnant, but couldn’t because of PCOS. She read How I Gave Up My Low Fat Diet and Lost 40 Pounds, went low carb, got pregnant, and carried the child to term. That’s the kind of thing that keeps me grinning for days.

Commonly, I hear of vastly improved blood work – one fellow had his triglycerides plummet by 1200 points in 2 weeks. People regularly report low trigs and high HDL.

Blood pressure reliably drops, too. It’s common for detractors to say “Oh, you only lost water weight on that diet.” That’s nonsense, of course, but it is true that the very rapid loss of 5-10 pounds in the first week or so is largely water. That’s because when insulin levels drop the kidneys resume excreting sodium properly, and with it the water it was holding. Because of this, blood pressure comes down quickly. (For this reason, people who are medicated for high blood pressure must be under a doctor’s care when they first go low carb. They may need a reduction in medication within days.)

By the way, the proper excretion of sodium means that many low carbers need to increase their salt intake – I’m one of them. If a new low carber is feeling tired, achy, dizzy, headache-y, the first thing to try is increasing salt – heavily salted broth or bouillon works wonderfully.

Energy swings vanish when the blood sugar swings stop. Many annoying symptoms of generalized inflammation, such as arthritis, are reduced or eliminated.

Gastroesophageal reflux, aka heartburn, generally clears up.

hqdefault (5)

And all kinds of little things – skin conditions, bleeding gums, stuff like that. My husband, who has a mouth full of crowns, hasn’t had a single new cavity since we went low carb 20 years ago. (I still have no fillings at the age of 57.)

Perhaps most surprising was the woman who wrote me to say that since she and her husband had gone low carb, a range of problems had cleared up, including that he had “stopped coughing up blood.” She finished with “You have been a miracle for our family.”

I have no idea how a low carb diet would stop the coughing up of blood, but I’m certainly glad it did.


Dana Carpender is the author of nine cookbooks, including the best-selling 500 Low-Carb Recipes.

Younger type one diabetics miss the most health checks

The England and Wales National Diabetes Audit is the largest annual clinical audit in the world and the most comprehensive of its kind. It gives information on how much of NICE policy is being implemented.

In the 2013-15 populations the percentage of registered diabetics has risen to 5.1% although it is thought that 7.1% of men and 5.3% of women have the condition from the Health Survey for England 2014.

Nine care processes are recommended by NICE.  Overall 39% of type one diabetics and 59% of type two diabetics got all of the checks covered in the audit. Worryingly only 27% of type ones under the age of 40 got all the necessary checks. There is a large range in variability in performance. For type ones in some areas 17% had all the checks and the best managed 62%.

Overall diabetics have a good chance of getting their bloods taken and blood pressure taken. The offer of structured education for newly diagnosed type one patients rose from 17% to 76%. Although 78% of type twos are offered structured education, only 5% take it up.

Only 30% of type one diabetics have glycaemic values of 7.5% HbA1c or 58 mmol/mol. Only 8.7% of type ones got 6.5% or 48 mmol/mol or below. 29% of type twos achieved this target.

The quality of care seems to be worse for type one diabetics especially in the younger age groups. Most of these people will be seen by hospital teams rather than a General Practitioner. The reasons why structured education is sidelined by patients is also mysterious.

Based on an article by Steve Chaplin Medical Correspondent for Practical Diabetes March 2016.

PD-Logo-WEB

Depression doubles stroke risk even when treated

Persistent depression is associated with twice the risk of stroke in adults over 50.

Researchers interviewed 16,178 people every two years from 1998 over a 12 year period and assessed depressive symptoms and stroke. They showed that those people who scored significantly for depression on at least two consecutive interviews had double the risk of having a first stroke in the two years after the assessment compared to those with low depressive symptoms. The risk was slightly higher for women and those who had had previous depressive symptoms.

Paola Gilsanz of Harvard University said, ” Our findings suggest that depression may increase stroke risk over the long term. This risk remains elevated even if depressive symptoms have resolved, suggesting a cumulative mechanism linking depression and stroke. Physiological changes may lead to vascular damage over the long term. Depression is also linked to hypertension, ill effects on the autonomic nervous system and inflammatory responses that all cause vascular disease. In addition depressed people are more likely to smoke and by physically inactive.”

4254385133_c983bfbb00_o

From Research News BMJ 23 May 2015


Diabetes duration and control affects intellectual decline


324468854_8f9fd42793_z

People who have diabetes diagnosed in midlife have a higher risk of cognitive decline over the following 20 years compared to people with normal glucose levels. A prospective study done in the USA showed that there was a 19% increased risk of cognitive decline over the 20 years for those who had diabetes. This meant that having diabetes aged cognitive function by about five more years than normal.

The level of decline was associated with the degree of control of the diabetes. Those with HbA1cs over 7% were more at risk than those with a better degree of control.  Increased duration of diabetes also led to a higher risk.

The study reviewed 13,351 year olds who were aged 48-67 at the start of the study for 20 years. Associate professor of epidemiology Elizabeth Selvin of John Hopkins University said of her findings, ” The lesson is that to have a healthy brain when you are 70, you need to eat right and exercise when you are 50. Maintaining cognitive function is a critical aspect of successful ageing. Preventing diabetes and improving glucose control in people with diabetes offers important opportunities for preventing cognitive decline and delaying progression to dementia”.


Study Shows Success of Low-Carb Diet

low-carb diet mealThe Daily Telegraph reported this week that a large pilot study of low-carb diets has suggested that they can successfully control type 2 diabetes.

That’s no news to us here at the Diabetes Diet, but the study is interesting because it involved a huge number of people – 80,000 of them, who gave up low-fat, high carbohydrate diets and found that their blood glucose levels dropped after 10 weeks.

That study was carried out after what was described as “an online revolt” by patients in which 120,000 people signed up for the “low-carb” diet plan launched by the global diabetes community website, diabetes.co.uk. The low-carb plan goes against official advice given by the NHS and Diabetes UK.

More than 80 percent of the people surveyed said they had lost weight, with 10 percent of them losing 9kg or more. More than 70 percent of the patients experienced improvements in their blood glucose levels and a fifth of participants said they no longer needed drugs to regulate their blood glucose levels.

The people taking part had followed diabetes.co.uk’s 10-week low-carb plan.

The website’s low carb plan is available here, but you can find plenty of help and advice for following a low-carb diet in our book, the Diabetes Diet. Our website also has lots of low-carb recipes – from starters, to main courses, snacks and sweets. Use the search button or check out the recipe category to find what you want.

Fasting Guidelines for Diabetics During Ramadan Update

empty plateThe International Diabetes Federation (IDF) has updated its advice about how to control diabetes throughout the annual fasting period of Ramadan.

This year, Ramadan starts on 6 June. The start and end dates depend on sighting of the moon. Ramadan is observed by more than 1billion Muslims each year and it commemorates the first revelation of the Quran to Mohammad.

The new guidelines have been drawn up by the Diabetes and Ramadan (DAR) International Alliance. They have been approved by the senior Muslim professor, Sawky Ibrhaim Allam.

During Ramadam, practising Muslims fast from dawn to dusk. The new guidelines say that people with diabetes should make the decision about fasting on an individual basis and in consultation with their physician.

The guidelines state that the decision should take in to account the severity of their illness and the level of risk. They also provide nutrition plans and medication adjustment suggestions that can be used during fasting.

The NHS recommends that people who control their diabetes using diet or tablets can fast with healthcare guidance, but advises those who use insulin to control their diabetes not to do so.

Eggs make a good start to the day


Eggs have been shown to improve satiety and increase circulating HDL. They contain nutrients that may reduce the risk of T2D and CVD. Current guidelines regarding egg consumption and dietary cholesterol intake differ among countries: Australia recommends a max of 6 egg/wk for people with T2D. The US recommends that patients with T2D limit dietary cholesterol to <300 mg/d and <4 eggs/wk; and the UK has no suggested limit, but they do emphasize a dietary reduction of saturated fatty acids. Previous studies regarding the effect of a high-egg diet had confounding factors and/or limitations with respect to data. Australian researchers decided to address those limitations by analyzing the health effects of a high-egg diet.

In a 3-month prospective RCT, 140 patients with BMI >25 kg/m2, and either prediabetes or T2D, were randomly assigned to 2 diet groups. Patients in the high-egg group consumed 2 eggs/day for 6 days/wk, while the low-egg diet group consumed <2 eggs/wk with 10 g lean protein for breakfast. The primary outcome was change in HDL cholesterol at 3 months, while changes in anthropometric measurements, vital signs, nutritional analysis, and satisfaction were all doneeggs secondarily. Blood samples were collected for FBG, HbA1c, lipid panel, C-reative protein, apolipoprotein B, CBC, thyroid function, liver and renal function. Height and waist circumference was measured and a patient food diary was collected at baseline and 3-months. Questionnaires were used to obtain food, physical activity and quality of life information from the patients.

The study results showed that there were no significant differences in HDL from screening to 3 months between the two groups. There were also no significant differences in total cholesterol, LDL, TGs, or apolipoprotein B. Both groups had no significant differences in FBG or HbA1c. Waist circumference, total body fat, fat free mass, BP, and HR did not show any significant differences. Both group had an increase in overall satisfaction with the diets they were on. However, the high-egg group showed a higher enjoyment with the food they were eating and were less bored with food options. The high-egg group also trended toward being more satisfied with a high-egg diet compared to a low-egg diet with a significantly greater satiety and less hunger reported after breakfast.

Previous studies and current guidelines do not provide a clear message as to the whether eggs are safe and suitable as a dietary protein source for people with T2D with a high risk for CVD complications. This study showed there were no significant differences in circulating HDL, LDL, TC, or TGs between the high- and low-egg diet groups. The high-egg diet group also showed a significantly greater food-acceptability score and scored their diet with less hunger and greater satiety after breakfast; this suggest that a high-egg diet does not result in boredom and may likely improve nutritional management in patients with T2D.

Practice Pearls:
•This study compared the health effects of a high-egg diet (2 eggs/day for 6 days/wk) with a low-egg diet (<2 eggs/wjk).
•The high-egg diet group showed no significant difference in their lipid panel at 3 months, compared to the low-egg diet group.
•Test patients showed a greater satiety after breakfast and greater food-acceptability in the high-egg diet, suggesting that a high-egg diet can be used to help improve nutritional management.

NR Fuller. The effect of a high-egg diet on cardiovascular risk factors in people with type 2 diabetes: the Diabetes and Egg (DIABEGG) study –a 3-mo randomized controlled trial. Am J Clin Nutr. 2015; 101: 705-713.


Based on an article in Diabetes in Control April 2016

Dr Peter Attia’s advice on dodging death

Do you want to live to a good old age? Researcher Dr Peter Attia discussed his top tips with paleo diet enthusiast Chris Kresser in March 16. This is summary of what he had to say.

Henny Nonne (geb. Heye), Max Nonne
Professor Max Nonne und Frau [Henny Nonne], geb. Heye
There are a few obvious big things that we can all do to dodge death at a prematurely.

  1. Choose to be a non- smoker.
  2. Don’t die by suicide.
  3. Avoid accidental deaths.  Most of these are caused by three things, Road Traffic Accidents, accidental poisoning, including the wrong use of prescription medication, and falls. You can minimise these by using a seatbelt, driving carefully, particularly at junctions, not using the phone when driving and avoiding any alcohol use at all when driving.  When you are a pedestrian be wary of drivers, cross the road in safe places and be very careful regarding alcohol intake.
  4. About 80% of all deaths in the over 40s are caused by the diseases of civilisation: atheromatous disease causing heart attacks and strokes, cancer and neurodegenerative disease such as Alzheimer’s and Parkinson’s disease.  Some of these have a genetic basis that we can do nothing about, but there are lifestyle measures you can take to delay or avoid them.
  5. Keep your blood glucose and therefore blood insulin levels low and with a low level of variability. A high fat, moderate to low protein and low carbohydrate diet is best for this. Dr Attia’s opinion is that 20% carb 20% protein 60% fat is about right.
  6. Avoid stress. There are two components to this. To feel fulfilled and happy you need meaning in your life. You will be happier if you can give support to others and receive it from them too. Minimise stress if you can. Consider meditation practice.
  7. Get a good sleep every night. Sleep deprivation causes severe insulin resistance. Keep the bedroom completely dark. Keep it cool to even cold. Avoid blue light from computers, phones or lights for several hours before sleep. Consider using melatonin, phosphatidylserine, magnesium, L-threonate and vitamin D to enhance your sleep if you are not sleeping well.
  8. Exercise. This has stress benefits of its own and also improves glucose uptake into the muscles if the right exercises are done. For best increase in muscle insulin sensitivity Peter advises squats and deadlifts done with good form and with very heavy weights.
  9. Decide what you are going to do for your optimum benefit and then change your habits so that they become second nature. Repetition is the key.
  10. 151985627_f76043167b_b.jpg